The Ultimate Inclusive Content Marketing Guide: Download Now
Learn how to create content that reaches your widest audience yet.

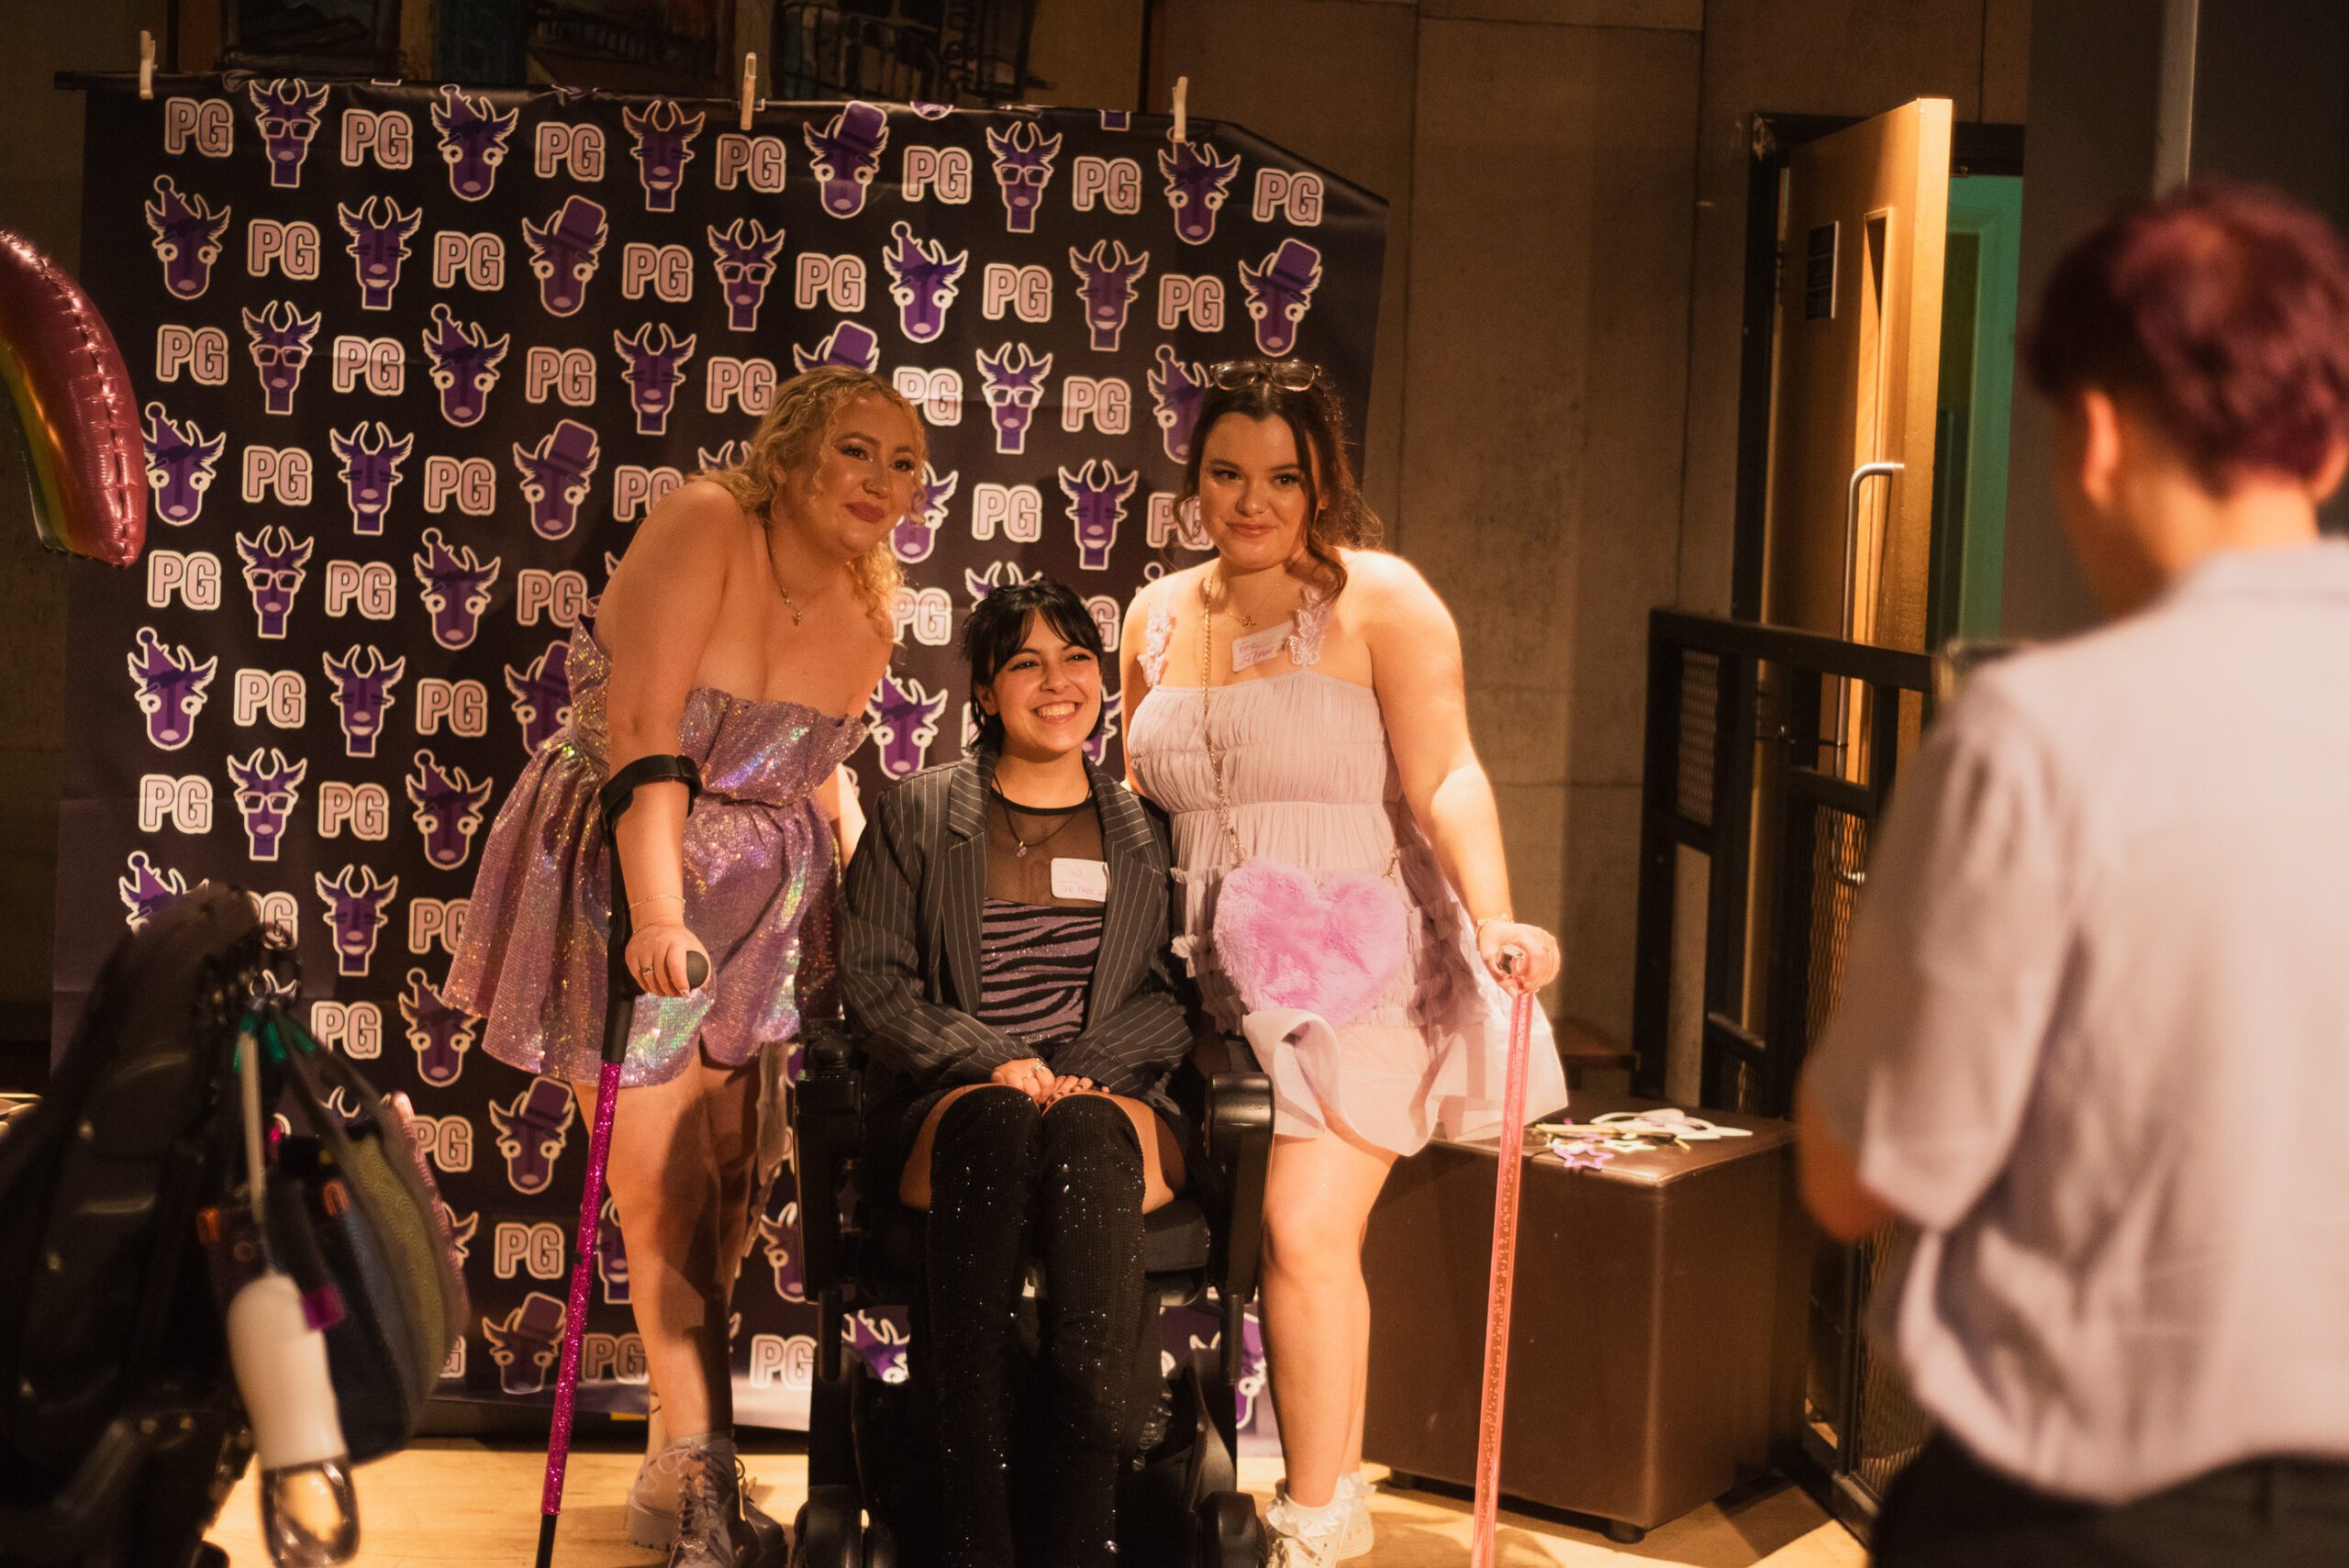

When it comes to planning any kind of DEI policy or approach, or even an event, which we have previously written about, disability is so often left off the agenda. When disability is discussed or acted on in terms of policy, the approach taken by a brand is often through a particular lens – or model – each with a different angle and impact. Understanding the models of disability is essential for organisations that want to move beyond surface-level inclusion and build meaningful, effective DEI strategies.
In this article, we will look at the different models of disability, why they matter, and why organisations should take these into account when executing any kind of DEI policy or approach. We’ve broken this down, as well as answering which model you should utilise the most, and why.
A model of disability is a framework used to understand disability, shaping how individuals, organisations, and societies perceive disabled people and respond through policy, environments, and behaviour.
In short, a model of disability is a lens used to view disability. The model that’s used can have a significant impact on the perception of disability, along with the actions taken in whatever environment we may be in. They are also not fixed – in that the model of disability being used may change throughout your day. The doctor’s office is different from when socialising with friends.
There are multiple models of disability, and these are just five of them:
The Medical Model of disability assumes that disability is a deficit in need of fixing or a cure, such as when it comes to using mobility aids. For example, using a wheelchair or other mobility aids is seen as a ‘failure’, something that the individual needs to overcome. Based on this model, disabled people cannot enjoy life, and are seen as dependent and a burden to others. This model can be reductive, and can lead to intrusion – such as with disabled people becoming a medical curiosity in a medical setting (“can’t you educate me about…?”, or when they find themselves on the end of questions like ‘what’s wrong with you?’
The Charity Model suggests that disabled people are a tragedy, as well as being pitiful individuals. They are reliant on the good will of other, non-disabled people, and are usually shown in a scenario of ‘passive’ suffering. The non-disabled people are the saviours, the heroes, of this model. While this model can be used effectively in terms of raising money through campaigns, we need to be asking ourselves if this is appropriate in 2025. Disabled people are not in need of saving, nor are they victims of their own making.
The Economic Model defines disability as an inability to work, and assesses how someone’s disability affects their productivity. In this scenario, work is defined in a traditional, arbitrary sense – the idea of going into an office and working a 9 – 5 job, otherwise it’s not a valid form of working. We often see this idea espoused whenever the benefits system is talked about; this model of disability is often seen when calculating the ‘cost’ gap of disability when it comes to working in direct comparison to someone who is non-disabled.
The Moral Model of disability ultimately suggests that being disabled is due to a moral failing, as well as being a result of lacking responsibility. This idea is sometimes found in particularly religious communities; it is a model that can also arise from superstitious beliefs.
The Social Model of disability suggests that, in opposition to the Medical Model, the lack of access in society is disabling. Developed and popularised by disability rights advocate Mike Oliver, this model argues that barriers in the built environment, attitudes, and systems are the primary causes of exclusion. This includes barriers in society such as inaccessible buildings, poorly designed transport, and exclusionary practices within the physical environment.
For example, the failure to provide a ramp at a restaurant door is disabling, as an individual who uses a mobility aid is unlikely to, or may be completely unable, to enter. The body is not at fault, and is not in need of correction – rather, it is the systematic barriers to access that are the issue. They are the failing that is in need of correction in this scenario.

The Models Of Disability inform a point of view, which then influences how policy is formulated – in turn impacting the lives of disabled people everywhere. For organisations who want to work with disabled people, it is important that they keep in mind these models of disability. DEI policy needs to tap into lived experiences, as well as avoiding a so-called ‘tick-box’ approach of inclusion and disability.
A lot more can be done than just having one disabled person being present in a room; this is not inclusion by any means, as one disabled person does not speak for every disabled person. These models of disability have also played a key role in shaping the disability rights movement and continue to influence disability policy and DEI policy today.
In the DEI space, the Social Model of Disability is usually the preferred model. This is because it encompasses disabled people as they are, all the while taking the appropriate levels of responsibility; disability should be viewed as a neutral concept, a part of being human. Society’s barriers impact disabled people’s lives, such as in blocking us from workplace opportunities, socialising, more – and we all have the ability to keep on learning how to support the disabled community. Concepts such as Universal Design, including features like step-free access and accessible toilets, are practical outcomes of applying the social model in real-world settings.
A Pan-Disability approach to the DEI space is the way to go, such as when it comes to planning events, hosting webinars, or during hiring processes. So, planning the inclusion from the start is the way to include everybody. Start by listening to feedback from disabled people, employ the expertise of disabled consultants across the board – and take the view of ‘how is society disabling in this very moment?’
While the models of disability can change depending on the setting/environment a person is in, it’s important that disabled people are given a voice at the table, and are given the due credence we all deserve. You don’t know what you’re missing otherwise!
If you want to learn how to approach disability in your organisation, reach out to the team at Purple Goat.
In the UK, the Social Model of Disability is the most widely used, particularly in policy, advocacy, and DEI work. The Medical Model is still common in healthcare settings, while the Charity and Economic Models continue to influence public attitudes, fundraising, and discussions around welfare and employment.
The social model of disability is important because it challenges the idea that disability is an individual problem. By reframing exclusion as a result of how society is organised, it supports more inclusive thinking and shifts responsibility towards systems, environments, and decision-makers.
Models of disability affect how DEI policy is developed and applied in practice. Medical or charity-led approaches often result in tokenism or limited adjustments, while the social model encourages systemic change and long-term accessibility across organisations.
Mike Oliver’s social model of disability argues that people are disabled by societal barriers rather than their impairments. Inaccessible environments, inflexible systems, and negative attitudes are identified as the primary causes of exclusion.
Applying the social model means designing inclusion from the start, addressing barriers across environments, communications, and policy. Listening to disabled people and working with specialist partners, such as Purple Goat, helps translate theory into meaningful action.

